
Composite bonding has become one of the most popular cosmetic dental treatments in the UK, and for good reason: it addresses a remarkably wide range of aesthetic concerns quickly, affordably, and with minimal intervention to healthy tooth structure. Yet many patients who could benefit from the treatment are not sure whether their particular concern is suitable for it, or they assume that more invasive options such as veneers or crowns are the only route to a noticeably better smile. The truth is that composite bonding is often the most appropriate first-line solution for a broad spectrum of cosmetic issues, and in some cases it can also serve a functional role — protecting vulnerable tooth surfaces or closing gaps that trap food and contribute to hygiene difficulties.
Chipped or Fractured Teeth
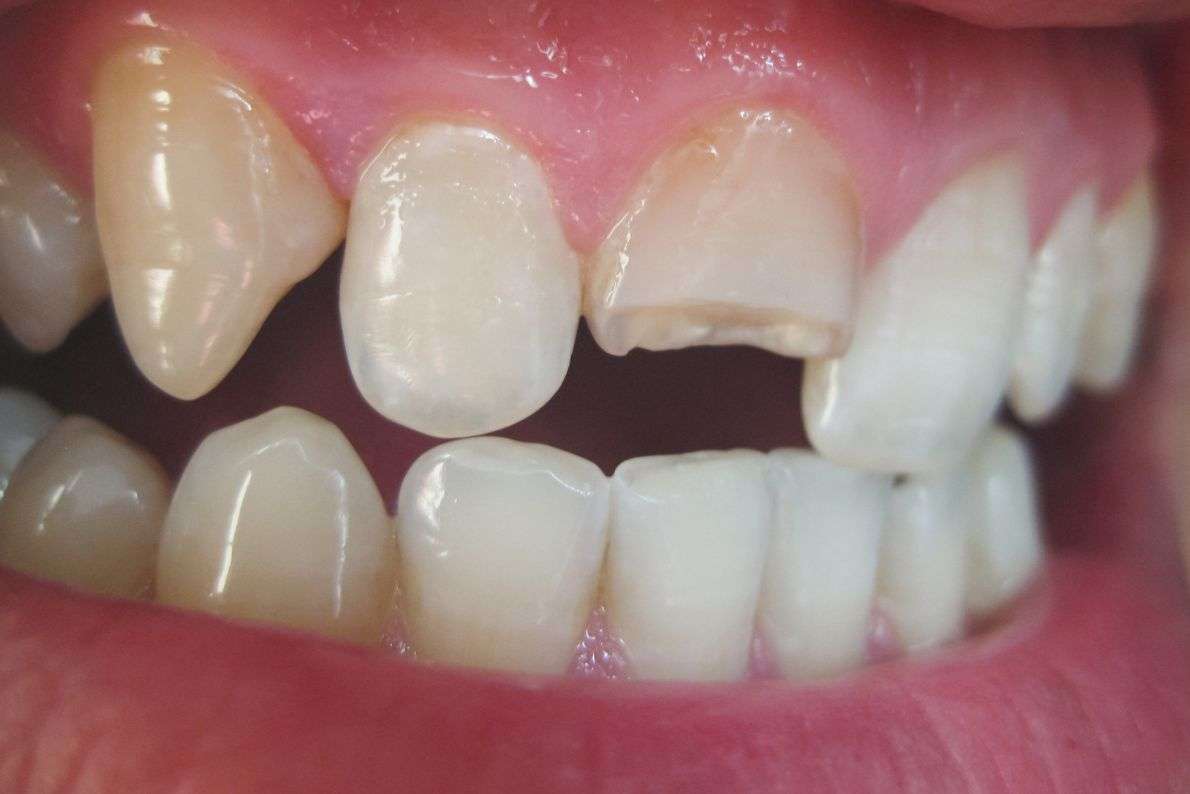
One of the clearest indications that composite bonding may benefit you is the presence of a chipped or fractured tooth. Chips most commonly affect the upper front teeth, which bear the brunt of minor impacts, but they can occur anywhere in the mouth. A chip does not need to be large or dramatic to benefit from bonding — even a small nick at the corner of a tooth can create a rough edge that irritates the tongue and draws the eye when you smile.
Composite resin is ideal for chip repair because it can be sculpted precisely to match the original tooth contour, and the material bonds directly to enamel without requiring any drilling of healthy tooth structure. The colour is matched to your natural teeth so carefully that most people cannot tell which tooth was treated. For larger fractures that extend deeper into the tooth structure, your dentist will assess whether bonding alone is sufficient or whether a crown or other restoration is more appropriate, but for the majority of cosmetic chips, bonding is the treatment of choice.
Discolouration That Whitening Cannot Address
Professional teeth whitening is an excellent treatment for most forms of surface staining and generalised tooth discolouration, but it is not effective for all types. Intrinsic discolouration — staining that originates within the tooth itself rather than on its surface — does not respond to whitening agents. Common causes of intrinsic staining include exposure to certain antibiotics (particularly tetracycline) during tooth development in childhood, dental fluorosis resulting from excessive fluoride intake, and discolouration following root canal treatment or trauma to the tooth.
When whitening will not work and a patient is self-conscious about the colour of one or more teeth, composite bonding offers an elegant solution. The dentist applies tooth-coloured composite resin over the front surface of the affected tooth, masking the discolouration completely. The result is immediate and, in skilled hands, virtually indistinguishable from a naturally white tooth. This approach is also far more conservative and affordable than porcelain veneers, making it accessible to a much wider range of patients.
Gaps Between Teeth (Diastema)
 A gap between the two upper front teeth — known as a diastema — is a common feature that many people find cosmetically bothersome. Smaller gaps can often be closed very effectively using composite bonding, by building out the edges of the adjacent teeth with carefully shaped and coloured resin until the gap narrows or disappears entirely. The procedure is straightforward, requires no preparation of the tooth, and can be completed in a single appointment.
It is worth noting that bonding is most suitable for closing gaps up to around two to three millimetres. Larger gaps may be better addressed through orthodontic treatment, which moves the teeth into a new position rather than building out the tooth surfaces. For patients who have already had orthodontic treatment and find that a small gap has persisted, or who have minor relapse after wearing a retainer, bonding is often the fastest and least disruptive way to achieve the smile they want.
Teeth That Are Smaller or Shorter Than Desired
Some patients have teeth that are naturally shorter than average, or that have worn down over time due to grinding (bruxism) or dietary acidity. Shorter teeth can give the smile a less youthful appearance, and in some cases they also affect the way the bite functions. Composite bonding can be used to add length to shortened teeth, restoring a more proportionate relationship between the teeth and the gumline and producing a fuller, more balanced smile.
Peg laterals — upper lateral incisor teeth that are unusually small and pointed — are another specific indication for bonding. These teeth are a relatively common developmental variation and can make the smile look less uniform. Building them out with composite to match the size and shape of the adjacent teeth makes a substantial difference to the overall appearance of the smile and is among the most satisfying cosmetic transformations that bonding can achieve.
Misshapen or Uneven Teeth
Not every tooth concern involves damage or discolouration. Some patients are simply unhappy with the natural shape of one or more teeth — perhaps a canine tooth is slightly pointed, an incisor edge is uneven, or the teeth lack the rounded, symmetrical appearance associated with an attractive smile. Composite bonding allows a dentist to add or refine tooth contour with a degree of precision that can meaningfully improve smile aesthetics without touching healthy enamel.
This application of bonding is sometimes described as smile sculpting or cosmetic contouring with composite, and it represents one of the purest expressions of what the treatment can achieve. In the hands of a dentist with experience in smile design, the results can be genuinely transformative, yet the treatment remains entirely reversible and leaves the underlying tooth structure completely intact.
Exposed Root Surfaces
Gum recession — whether caused by aggressive brushing, gum disease, or natural ageing — can leave the roots of the teeth partially exposed. Root surfaces are not protected by enamel and are therefore vulnerable to sensitivity, discolouration, and erosion. Composite bonding can be applied to exposed root surfaces to cover them, reducing sensitivity and improving appearance. While this is not strictly a cosmetic application, it often has cosmetic benefits alongside the protective function, and it is a less invasive alternative to surgical gum grafting in many cases.
For more information about the range of dental treatments available in the UK and when they are appropriate, the NHS guide to dental treatments provides a clear and impartial overview of options across the spectrum of dental care.
When Composite Bonding May Not Be the Right Choice
While composite bonding is versatile, it is not universally appropriate. Patients with severely misaligned teeth may find that orthodontic treatment delivers better long-term outcomes, as bonding cannot correct the underlying position of the teeth. Patients who grind heavily and do not use a night guard may find that composite chips or wears more quickly than desired. And for concerns that affect a large number of teeth, or where significant underlying structural issues exist, a more comprehensive treatment plan may be needed before or instead of bonding.
This is why a thorough consultation with an experienced dentist is so valuable. A good consultation will not simply assess whether bonding is technically possible, but whether it is genuinely the best option for your specific teeth, bite, and aesthetic goals.
Composite Bonding Suitability at a Glance
| Dental Concern | Is Composite Bonding Suitable? | Alternative if Not |
|---|---|---|
| Chipped or broken tooth edge | Yes — ideal for minor to moderate chips | Crown (for major fractures involving the pulp) |
| Intrinsic tooth discolouration (e.g. tetracycline staining) | Yes — effective at masking internal staining | Porcelain veneers (for severe cases or whole arch) |
| Small gap between front teeth (up to ~3mm) | Yes — can close gap by building out tooth edges | Orthodontics (for larger gaps or bite issues) |
| Shortened or worn teeth | Yes — can restore length and shape | Crowns or onlays (if structural damage is extensive) |
| Peg lateral incisors or small teeth | Yes — excellent results with sculpting technique | Porcelain veneers (if patient prefers longer-lasting option) |
| Exposed root surfaces / gum recession | Yes — covers root and reduces sensitivity | Surgical gum graft (for severe recession) |
| Generalised surface staining | Possibly — whitening is usually preferable first | Professional teeth whitening |
| Significant tooth misalignment | No — bonding cannot correct tooth position | Orthodontics (braces or clear aligners) |
The Importance of a Proper Assessment
Many patients come to a consultation already having decided they want composite bonding, having researched the treatment online or seen results on social media. While enthusiasm for a treatment is a good starting point, it is always worth approaching any cosmetic procedure with openness to professional guidance. A dentist with experience in cosmetic dentistry will assess not only the teeth themselves but also the gum health, bite, and overall oral condition before recommending a treatment path. If gum disease or significant decay is present, these need to be addressed before any cosmetic work is undertaken — and a reputable practice will always prioritise your dental health above cosmetic outcomes.
At Essential Dental Care in Polwarth, Edinburgh, we offer detailed smile consultations where we listen to your concerns, examine your teeth, and explain honestly which treatments are most likely to achieve the results you are looking for. We will always tell you if composite bonding is the right solution — and equally, we will tell you if something else would serve you better. To arrange a consultation, call us on 0131 229 1806 and our friendly team will be happy to help.
 For a single tooth — such as a chipped front incisor or a slightly discoloured lateral incisor — a composite bonding appointment typically takes between 45 minutes and one hour from the moment you sit in the dental chair to the moment the finished tooth is polished. This includes the time needed for shade selection, surface preparation, the layered application of composite resin, bite checking and fine adjustment, and final polishing. In some straightforward cases, particularly where only the edge or a small surface area of a single tooth is being restored, the treatment can be completed in 30 to 40 minutes. If the tooth requires more extensive reshaping — for example, building up a peg-shaped lateral incisor to a more normal width and length — the appointment may run to 60 to 75 minutes.
 Yes, but the consultation is typically separate from the treatment appointment. A thorough composite bonding consultation — including clinical examination, discussion of your goals, shade assessment, and treatment planning — generally takes 30 to 45 minutes. Some patients, particularly those with uncomplicated single-tooth concerns, may have their consultation and treatment combined into a single appointment if the dentist is satisfied that bonding is clearly appropriate and no further investigation is needed. For more involved cases, particularly full smile makeovers or situations where the bite or gum health requires assessment, the consultation is best kept as a standalone appointment so that the dentist can review the situation fully before committing to a treatment plan.
 If you would like to find out exactly how long composite bonding would take for your specific teeth and the results you are hoping to achieve, we would be happy to go through it with you in detail. At

 The single most important requirement for composite bonding candidacy is that the underlying teeth and surrounding gum tissue are in good health. Composite resin is a cosmetic material applied to the outer surface of a tooth, and it cannot compensate for, conceal, or protect a tooth that has active decay or structural compromise. If there is untreated caries present, the decay will continue to progress underneath the bonding material, potentially causing far more serious problems than if the cosmetic work had simply been deferred. Similarly, if gum disease is active at the time of treatment, the gum tissue is likely to continue receding or becoming inflamed, which will expose the margins of the bonding and undermine both the appearance and the integrity of the restoration over time. A dentist will always carry out a thorough examination before any cosmetic work and will insist that any active disease is treated and stabilised first. Patients who are committed to good oral hygiene and have no active dental problems are the most straightforward candidates.
 Standard tooth whitening works by bleaching chromogens from within the enamel, which is effective for the extrinsic and mild intrinsic staining that most people accumulate through diet and age. However, some types of discolouration do not respond to whitening at all. Tetracycline antibiotic staining, which occurs when the drug is taken during childhood while the permanent teeth are developing, creates a grey or banded discolouration deep within the dentine that bleaching cannot remove. Similarly, fluorosis — a mottled, white or brown patterning caused by excess fluoride during tooth development — and discolouration caused by a previous root canal treatment or internal bleeding within a tooth are not responsive to conventional whitening. Composite bonding can cover all of these types of discolouration effectively, masking the affected surface with a well-matched resin that restores a natural tooth colour. For heavily stained or darkly discoloured teeth, porcelain veneers may provide a more reliable long-term barrier to staining, and the dentist will discuss the relative merits of each option at consultation.

 Perhaps the most clinically significant benefit of composite bonding is that, in the vast majority of cases, it requires no removal of healthy enamel. Enamel is the hard outer layer of the tooth, and it does not regenerate once lost. Treatments such as porcelain veneers and dental crowns require the dentist to remove varying amounts of this irreplaceable material in order to create space for the restoration to sit flush. With composite bonding, the resin is added onto the existing surface of the tooth and shaped from there. The preparation involved is usually limited to a mild surface etch using a conditioning gel that helps the resin adhere effectively. This means the natural tooth underneath remains structurally intact, and if circumstances ever changed — if the bonding needed to be removed, for example, or if you wanted to switch to a different treatment in the future — the underlying tooth has not been permanently altered. For patients who are cautious about committing to irreversible procedures, this aspect of composite bonding is often the deciding factor.
 The quality of composite resin materials available to dentists today is substantially higher than it was even a decade ago. Modern composites are available in a wide range of shades and translucencies, allowing dentists to match the natural colour, depth and luminosity of real teeth with considerable precision. In the hands of an experienced cosmetic dentist, composite bonding produces results that are virtually indistinguishable from natural tooth enamel in everyday social situations. Photographs, conversation distances and normal lighting conditions do not reveal bonded teeth as artificial. This level of aesthetic refinement depends significantly on the skill of the clinician and the quality of the materials used, which is why choosing a dentist with demonstrable experience in cosmetic bonding work is important. For more background on how composite materials are developed and used in dentistry,